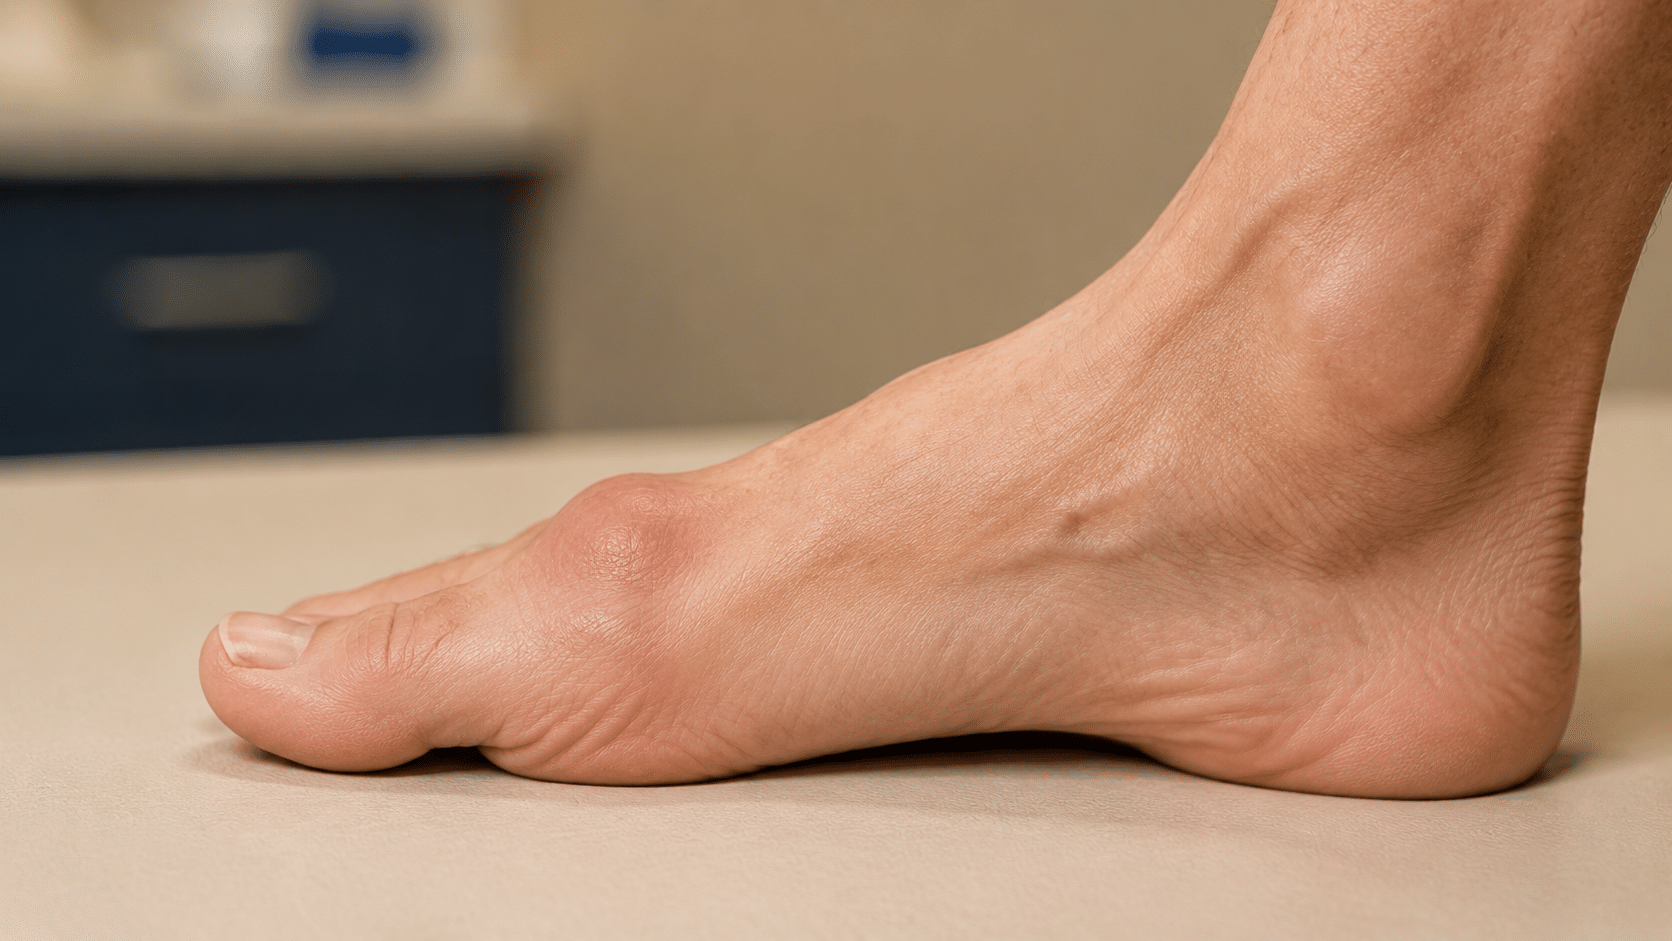
What Will Forefoot Surgery Recovery Actually Require From Your Life?
Most patients do not come to my office afraid of an incision. They are afraid of becoming unavailable to the people and responsibilities that depend on them.
They want to know whether they will be able to walk into the kitchen, drive to work, care for a parent, take a child to school, attend a meeting, or put on a normal shoe. “How long is recovery?” is usually shorthand for a much more personal question: How much of my life will I have to surrender in order to fix my foot?
That deserves a more useful answer than a generic number of weeks.
There Is No Single Foot-Surgery Timeline
Recovery is not determined by the diagnosis alone, and it is not determined by the incision size alone. I think about three interacting variables.
The first is the structural healing demand. A limited correction and a complex multiplanar reconstruction do not ask the same thing of bone and soft tissue.
The second is the patient’s baseline biology. Circulation, metabolic health, nutrition, bone quality, medications, smoking history, and other individual factors can materially affect healing.
The third is the recovery environment designed around the first two: stabilization, swelling management, biologic support when justified, communication, follow-up, mechanical protection, and the pace at which activity is reintroduced.
Minimally invasive technique can change the starting point by reducing unnecessary soft-tissue disruption. PRISM™ is how I coordinate the rest of the process. Neither makes biology disappear.
Walking Immediately Is Not the Same as Being Healed
In my practice to date, every bunion patient treated with my current minimally invasive protocol has been able to begin protected weightbearing immediately in the prescribed postoperative footwear. This is an observed practice result, not a promise of unrestricted activity or a guarantee for every future patient.
That is an observed result in my practice, not a promise that every future patient or every type of foot operation will follow the same course. It also does not mean unrestricted walking. The correction still needs protection, swelling still occurs, and bone and soft tissue still need time to heal.
The practical advantage is that recovery begins with protected mobility rather than automatically beginning with prolonged non-weight-bearing.
When Can I Return to a Regular Shoe?
In my practice, more than 90% of patients undergoing the forefoot procedures I perform have transitioned from postoperative footwear into a regular supportive shoe at approximately two to four weeks. “Regular shoe” means a supportive everyday shoe—not a dress shoe, heel, or unrestricted footwear. Some are ready near the early end of that range, others near the later end, and some appropriately require more time.
The shoe transition is based on the correction, swelling, incision and soft-tissue status, stability, and the patient’s individual healing response. It is a clinical milestone—not a date to chase.
When Can I Drive?
Driving depends on which foot was treated, the vehicle, prescribed postoperative footwear, pain medication, reaction time, and the patient’s ability to brake safely and confidently. A patient with left-foot surgery and an automatic vehicle faces a different problem from a patient whose right foot operates the pedals.
Many appropriately selected patients return to driving within days, depending on the treated foot, vehicle, protective footwear, medication use, and ability to perform an emergency stop safely. Patients must not drive while taking opioids or other sedating medication and must follow their individualized surgery-center and postoperative clearance instructions. We plan for that distinction before surgery, because transportation is not a minor detail when work, children, or caregiving responsibilities depend on it.
When Can I Return to Work?
The job matters as much as the foot.
Patients in remote or primarily seated work often resume selected responsibilities within days when elevation and activity control are feasible. A surgeon, nurse, teacher, contractor, or anyone who stands and walks throughout the day may need a different plan.
“Return to work” also should not mean merely being physically present. The goal is to return without creating swelling, fatigue, or mechanical stress that repeatedly sets recovery back.
When Can I Exercise Again?
Low-demand activity and full athletic return are different milestones. Many patients achieve full return to ordinary daily physical activity within approximately two to six weeks, depending on the correction and healing response. Impact activity, running, and sport-specific loading require evidence that the reconstruction can tolerate those forces and generally follow a separate progression.
Pain often improves before structural healing is complete. Feeling good is encouraging, but it is not permission to skip the biological timetable.
Why Recovery Has to Be Designed Before Surgery
The best time to discover that a patient must drive, care for a spouse, climb stairs, travel for work, or return to a particular shoe is not after the operation.
Those realities belong in the surgical plan from the beginning. During a comprehensive consultation, I want to understand not only the X-ray but the destination: what the patient is trying to reclaim, what cannot be disrupted, and which parts of recovery require the most support.
That is the role of PRISM™. The operation corrects the structure. The recovery system coordinates the environment around healing so the patient is not left to assemble the process after surgery.
The Most Useful Timeline Is Your Timeline
If you are postponing surgery because recovery feels impossible, the next step is not committing to an operation. It is replacing a vague fear with a specific plan.
Start with the Complete Bunion Decision Guide if you are still deciding whether treatment is warranted. If the problem is already limiting your life and you want to understand what walking, driving, work, footwear, and activity could look like for your particular correction, schedule a discovery call with Dr. Michael Tagge.