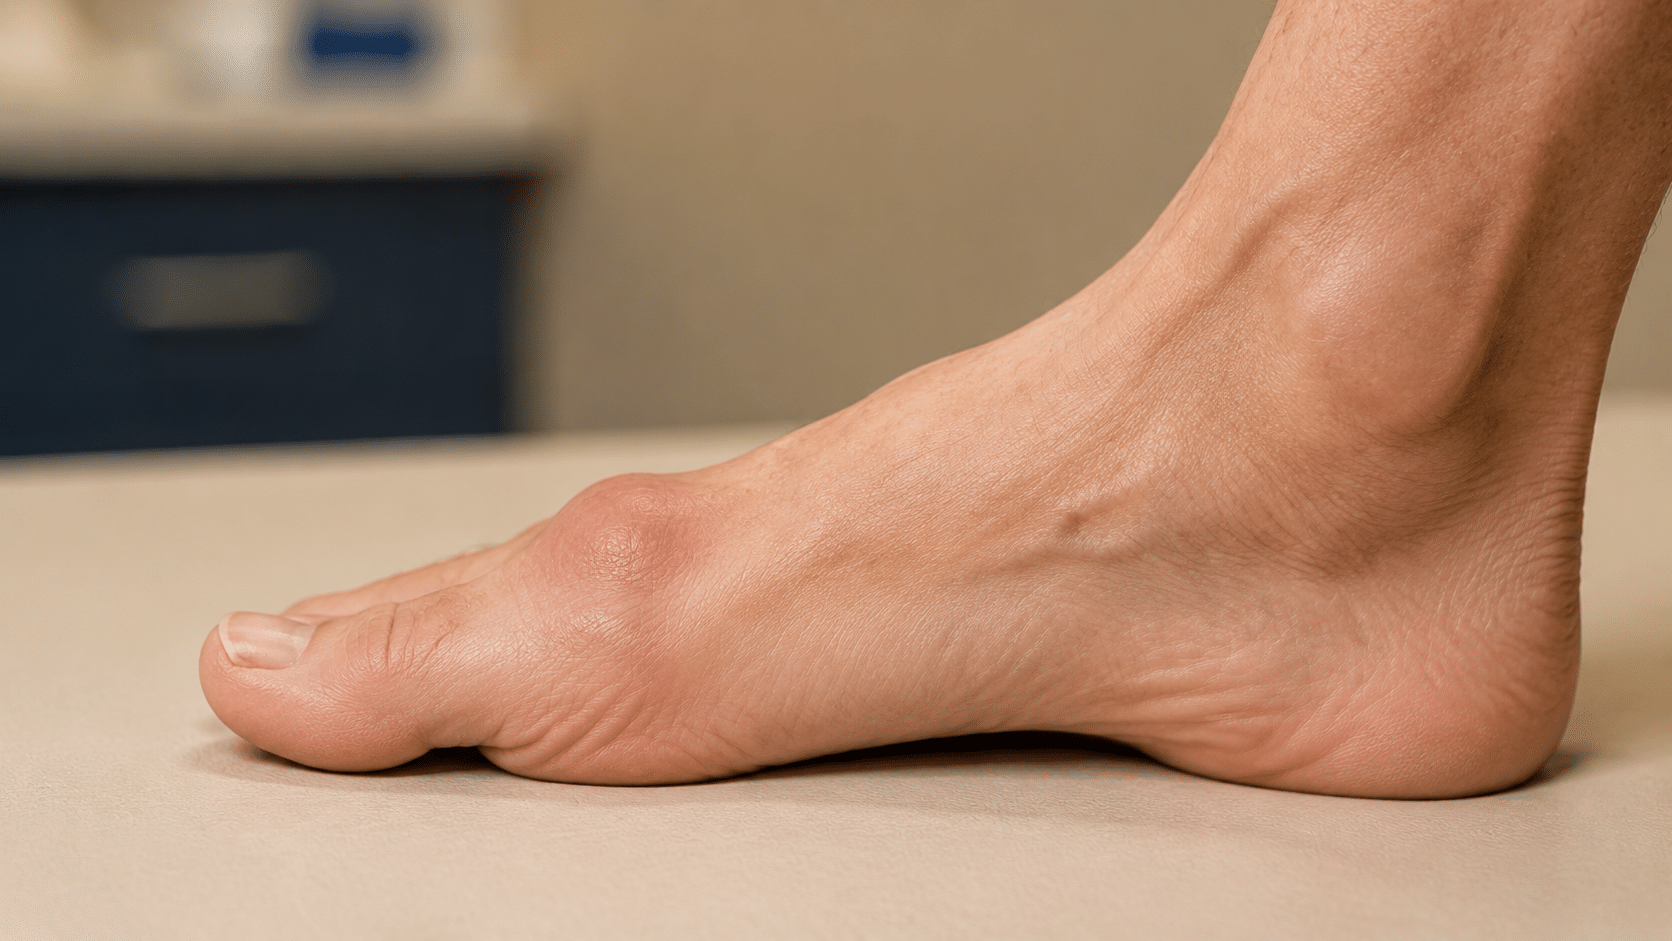
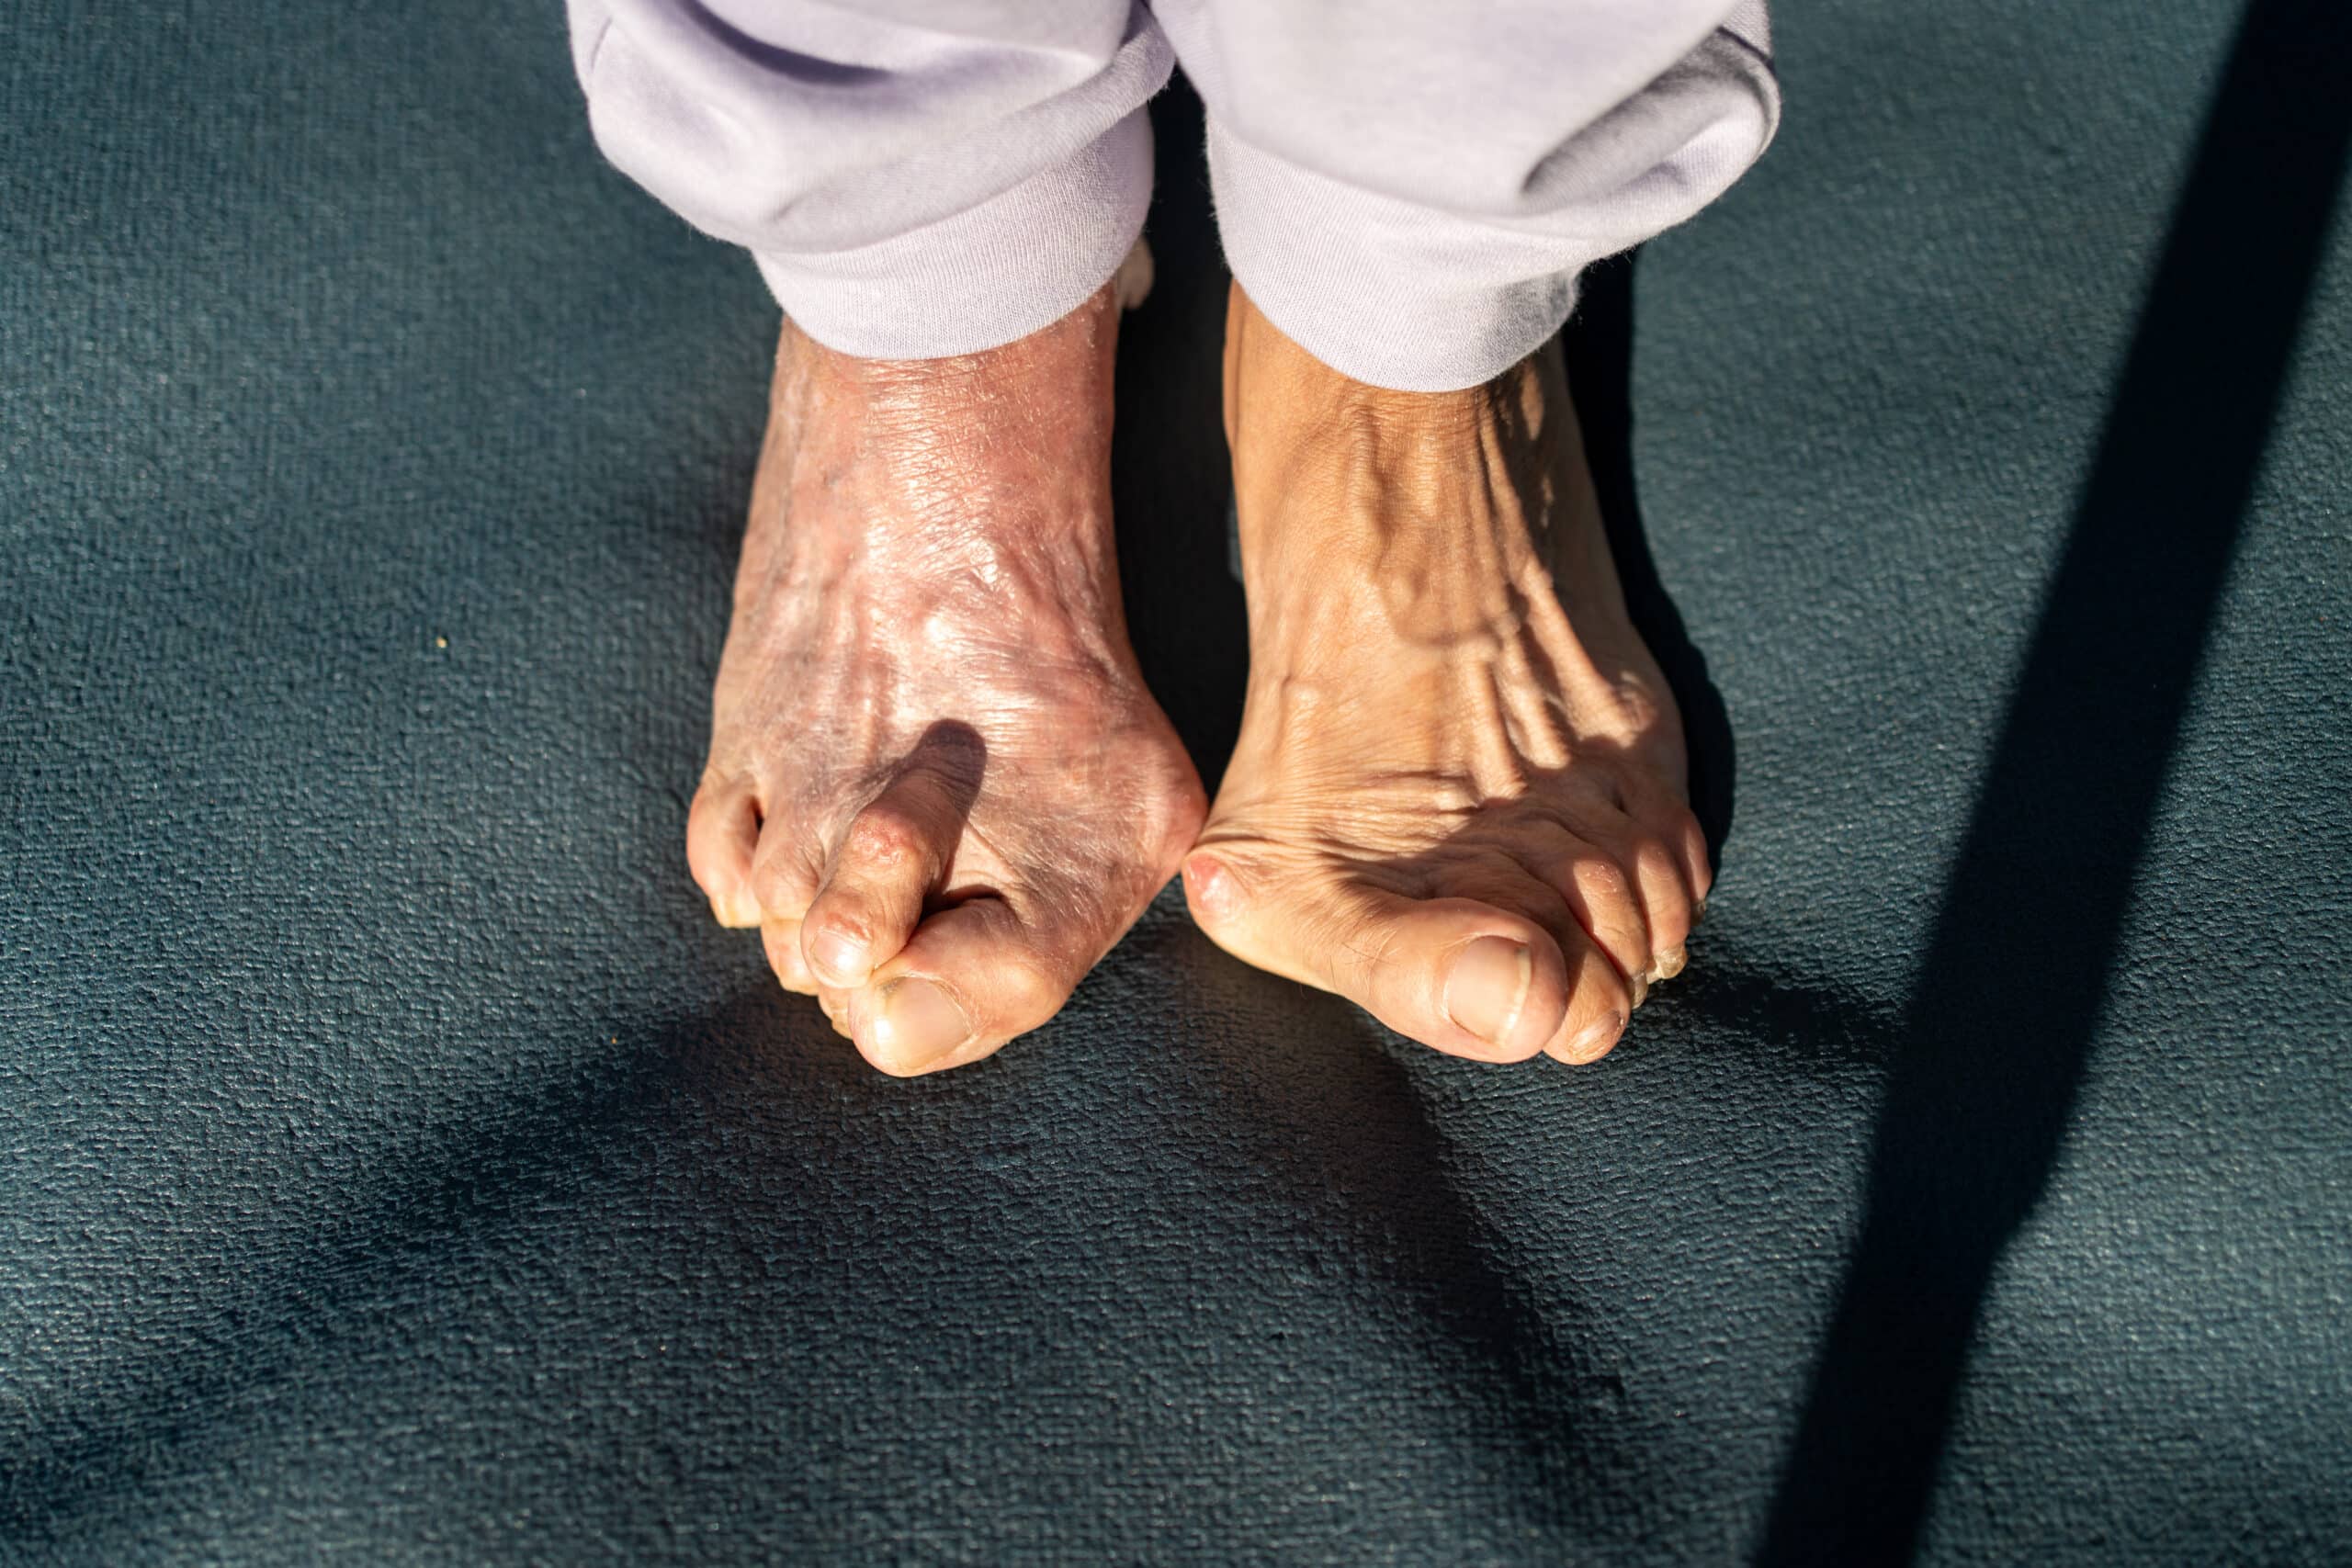
Foot surgery should do more than improve an X-ray. The real question is what the corrected foot allows you to do with your life afterward.
Most patients considering foot surgery are not really wondering what their postoperative X-ray will look like. They are wondering what their life will look like.
Will I walk normally again? Will I be able to travel? Can I get back to exercise? Will I wear the shoes I want? How much work will I miss? Will I still be able to take care of my family? If I am older, will surgery help preserve my independence or threaten it?
Those questions are not secondary to the operation. In many ways, they are the reason for having the operation at all.
I think one of the weaknesses of procedure-centered medicine is that it can become very good at defining a structural problem without spending enough time defining what a successful outcome actually means to the person living with it. A surgeon can measure an angle, reposition a bone, and produce an excellent-looking X-ray. Those things matter, but the person attached to that foot still has to recover, walk, work, wear shoes, travel, exercise, and live with the result.
That is why I want to understand the destination before I choose the route.
If you are still deciding whether your bunion has reached the point where treatment is worth considering in the first place, begin with the Complete Bunion Decision Guide: When to Wait and When to Act.
The same foot problem can mean very different things to different people
An X-ray can tell me a great deal about a foot. It can show alignment, deformity, arthritis, bone structure, joint position, and the mechanical relationship between different parts of the forefoot. What it cannot tell me is what that foot needs to do for you.
A 52-year-old woman who wants to return to tennis and a 79-year-old woman who wants to continue living independently may have very similar-looking bunions. Structurally, I may see many of the same problems. Functionally, those patients are asking me for two very different things.
For the first patient, success may mean restoring enough comfort, motion, stability, and confidence to return to lateral movement, athletic footwear, and regular exercise. For the second, success may mean being able to walk through a grocery store, travel to see family, remain steady on her feet, and continue managing her own life without becoming dependent on others.
Neither goal is more legitimate than the other. The important point is that the destination should affect how I think about treatment.
This is also why I do not believe pain scores alone tell us whether a foot problem has become significant. Patients are remarkably good at adapting. They stop wearing certain shoes, shorten their walks, modify workouts, avoid trips with too much walking, sit more often at events, or quietly organize their days around what the foot will tolerate. Because the changes happen gradually, they may not even recognize how much they have given up.
One of the questions I often find more useful than “How much does it hurt?” is, “What have you stopped doing because of your foot?”
The answer usually tells me far more about what treatment might actually give back.
The goal is not simply to remove a limitation. It is to restore choices.
A successful reconstruction should ideally expand the patient’s options rather than continue narrowing them.
For one person, that means taking a long walk without thinking about whether the foot will hurt afterward. For another, it means booking a trip without worrying about how far the airport gate is from security. Someone else may want to return to tennis, Pilates, running, strength training, golf, or simply a daily walk that used to be effortless.
Sometimes the desired outcome is less dramatic but just as meaningful. A patient wants to get through the workday without shifting from foot to foot. She wants to go to dinner without bringing a second pair of shoes. She wants to stand at a family event without constantly looking for somewhere to sit.
Those are ordinary things. That is exactly why they matter.
Most patients do not want to become experts in their own bunion surgery. They want the foot to eventually stop demanding so much attention.
That is the deeper goal: not simply making an activity possible again, but making it ordinary again.
If your primary concern is the actual timing of walking, shoes, work, driving, and exercise during recovery, see the complete foot surgery recovery timeline.
Shoes, appearance, and confidence are legitimate outcomes too
Patients sometimes hesitate to tell me how much footwear matters because they are worried it sounds cosmetic or superficial.
I do not see it that way.
Shoes are part of daily life. They are part of work, social events, exercise, personal style, and in many cases a person’s confidence. When a bunion progressively reduces the number of shoes someone can comfortably wear, that is a real quality-of-life change.
Many women describe the same pattern. They have a closet full of shoes, but only a small group they can actually tolerate. They bring a second pair to an event because they know their feet will not last the evening. They stop wearing shoes they once enjoyed because the bunion simply will not fit comfortably anymore.
A successful reconstruction should ideally expand those choices.
That does not mean I promise that every reconstructed foot will tolerate every possible shoe. Footwear still has to respect anatomy, mechanics, and the type of reconstruction performed. But it is entirely reasonable for footwear goals to be part of the conversation before surgery.
The same is true of appearance. Bunions and hammertoes can make patients self-conscious in sandals, barefoot, or in certain types of shoes. Wanting a foot that looks more natural does not make someone vain. If the appearance of the deformity is part of why the problem affects their life, then appearance is one of the outcomes worth discussing.
Function and appearance do not have to be competing goals.
Returning to activity should be considered before surgery, not after it
For active patients, exercise is often much more than exercise.
Running may be stress relief. Tennis may be a social life. A morning walk may be how someone clears their head. Strength training may be central to how they maintain health and independence. Cycling, golf, pickleball, hiking, or Pilates may simply be part of who they are.
I want to know those things before surgery.
The old model of thinking would be to choose the technically appropriate operation first and then, after healing, tell the patient what they are allowed to do. I prefer to understand what the patient is trying to return to before I design the reconstruction.
That does not mean the patient’s wishes override anatomy or biology. They do not. But their goals should influence the way I think about correction, mechanics, recovery, and long-term support.
It also affects how I think about mobility during the recovery itself. One of the advantages I value most in my minimally invasive approach is the ability, when the reconstruction safely permits it, to preserve protected weight bearing from the beginning.
That matters because an active patient is not only worried about the healing foot. They are worried about what happens to the rest of their body while the foot heals. Weeks of unnecessary inactivity can mean loss of conditioning, strength, mobility, and confidence that then have to be rebuilt later.
My goal is not simply to get someone walking for the sake of saying they walked after surgery. It is to preserve as much safe function as possible so the patient has less physical ground to regain when higher-level activity becomes appropriate.
You can see how this philosophy was applied to a real patient in how one patient returned to running after forefoot reconstruction with a recovery designed around his goal.
Work, travel, and caregiving are part of the medical history
Work is another area where generic timelines can become misleading.
Someone who works remotely and can elevate intermittently has a very different recovery problem from a teacher who stands all day, a nurse walking a hospital floor, a contractor climbing ladders, or an executive who spends half the month flying.
That is why I want to know what a patient’s work actually requires rather than simply knowing their job title. The goal is not merely to get someone physically back into the workplace. It is to get them back to doing their job without the foot becoming the central problem of the day.
Travel exposes the same issue in a different way. At home, patients become very good at adapting around a painful foot. They know where to park, which shoes work, when they can sit, and how much walking they can tolerate.
Travel removes those controls.
Airports are large. Vacations involve unfamiliar cities, longer days, more walking, standing, and often footwear that is different from what someone uses at home. I have had many patients tell me that a trip was the moment they finally realized how much their foot was limiting them.
The goal of treatment is not simply to make someone medically capable of going on vacation. Ideally, the foot stops determining what kind of vacation they are willing to take.
Caregiving creates another layer. Some patients delay treatment for years because other people depend on them. They are caring for children, parents, a spouse, or sometimes all three. Their fear is not only, “How much will this hurt?” It is, “What happens to everyone else if I cannot function?”
That question belongs in the surgical plan.
A caregiver may need temporary help during recovery, but the amount of disruption should still be proportional to what actually needs to be corrected. When protected mobility can safely be preserved, it can make the difference between being completely dependent and remaining meaningfully functional while healing occurs.
For older patients, the outcome may be preserving what they already have
Some of the most important conversations I have are with patients in their seventies and eighties who are not trying to reclaim an athletic identity. They are trying to protect the life they still have.
They may be living independently, driving, traveling, shopping, walking every day, golfing, gardening, caring for a spouse, or spending time with grandchildren. They understand that they are older. Their goal is not to pretend otherwise.
Their concern is that a painful foot is gradually narrowing their independence, while surgery could temporarily threaten that independence even more.
This is where fear of immobility becomes very real. Many older adults have watched a spouse, friend, or family member become weaker after an illness or prolonged period of inactivity. They understand intuitively that once strength, balance, and confidence are lost, they are not always easy to regain.
Some tell me very plainly that they are afraid of getting into a wheelchair and never really getting back out.
I take that seriously.
When a reconstruction safely allows protected weight bearing, preserving mobility may help limit unnecessary deconditioning and allow the patient to retain more strength and confidence while the foot heals. That does not mean every older patient should walk immediately after every foot operation. If the reconstruction requires restriction, then it needs to be protected.
But when I can accomplish the correction while preserving safe mobility, I consider that a meaningful advantage.
For the athlete, that may mean less conditioning to rebuild. For the older patient, it may mean helping preserve the capability necessary to remain independent.
The principle is the same: protect the reconstruction without unnecessarily sacrificing the rest of the patient.
A technically successful operation is not the same thing as a successful patient outcome
This is one of the core ideas behind the way I practice.
Surgeons have objective ways to measure what we do. We can measure angles, alignment, bone healing, joint position, stability, and recurrence. Those are important measures and I care deeply about them.
But objective measures are not automatically the patient’s objective.
If the patient’s reason for surgery was to return to walking, travel, exercise, work, or footwear, then those outcomes also matter. A beautifully corrected X-ray that does not meaningfully solve the problem the patient came in asking me to solve is incomplete information.
The reverse is true too. I would not sacrifice structural quality simply to make the early recovery look impressive. A reconstruction has to be durable and mechanically sound.
The goal is to design those two objectives together: a technically strong correction and a result that makes sense in the patient’s actual life.
That is one of the reasons I developed PRISM™.
Why PRISM™ matters after the operation is over
PRISM™ is not simply a way of performing minimally invasive surgery. It is the framework I use to think about the entire reconstruction.
The structural correction matters, but so does the patient’s capacity to heal it. The correction has to remain stable while healing occurs. The reconstructed foot eventually has to accept load appropriately. Recovery needs to preserve as much function as safely possible, and the long-term mechanics should support what the patient wants to do afterward.
Those are interconnected problems.
That is why I use the simpler patient-facing concept of Root → Fix → Heal. First, understand why the problem exists and what it is doing to the patient’s life. Then perform the correction that is actually necessary. Finally, deliberately support the biological, structural, mechanical, and functional process that follows.
The five PRISM™ pillars provide the deeper framework behind that philosophy, but the important point for this discussion is simple: I do not view the operation as the entire treatment.
What does not change after foot surgery
There is another side of this conversation that is important because I do not believe in selling surgery as magic.
A reconstructed foot still has anatomy. It still has to heal. It still has to tolerate load. It continues to age.
Correcting a bunion does not erase arthritis in other joints. Surgery does not make an older patient biologically younger. A high-level athlete still has to progress back to sport appropriately. Some patients will continue to benefit from thoughtful footwear or custom orthotic support because the corrected foot still has to function mechanically for years afterward.
That honesty is important.
My objective is not to create an artificial “perfect foot.” It is to solve the problem that is meaningfully limiting the patient’s life while preserving as much normal function as reasonably possible.
This also means that the operation should not end the conversation about mechanics. Every step still requires the forefoot to accept and transfer load. The great toe, lesser toes, metatarsals, arch, ankle, and rest of the lower extremity all influence how pressure moves across the foot.
The surgery addresses the structural problem. The long-term plan should help the patient use and protect the correction.
Treatment burden should be proportional to what we expect to gain
Elective surgery gives us something extremely valuable: time to think.
We can evaluate the deformity, understand the mechanics, look at the patient’s health and healing capacity, discuss alternatives, define what the patient actually wants to regain, and then ask whether the expected improvement justifies what treatment will require.
Sometimes the answer is no.
If a patient’s limitation is minimal and the burden of surgery would be disproportionate to the likely benefit, continued observation may be entirely reasonable. Sometimes a smaller operation can accomplish the patient’s actual goal without creating unnecessary disruption. In other cases, the patient’s life has become limited enough that the burden of continuing to adapt around the problem has become greater than the burden of correcting it.
That decision cannot be made from an X-ray alone.
It requires judgment.
I think that is particularly important in foot surgery because patients often assume the question is simply whether the deformity is “bad enough.” I would rather ask whether the problem is taking enough from the patient’s life, whether we have an appropriate correction, and whether the expected outcome is worth the recovery required to achieve it.
If you are still working through that decision, read the Complete Bunion Decision Guide: When to Wait and When to Act.
What life after successful foot surgery should ultimately feel like
The best outcome is often less dramatic than people expect.
You put on your shoes without having a negotiation with your foot first. You go to work without thinking about where you can sit. You walk through an airport without wondering whether you will regret it tomorrow. You exercise because you want to exercise, not because you are constantly modifying around pain.
An older patient keeps shopping, driving, traveling, or caring for a spouse without feeling that the foot is slowly shrinking the boundaries of independence.
Eventually, the surgery itself should fade into the background.
The patient should not remain a “bunion surgery patient” forever. The operation should become something that happened, not something that continues to define the person’s daily life.
That is what I mean when I say that the patient’s life is the outcome.
The X-ray matters. The correction matters. Healing matters. Stability and mechanics matter.
But ultimately, all of those things are in service of something larger: what the patient is able to do with the foot afterward.
Frequently Asked Questions About Life After Foot Surgery
Will I be able to live normally after bunion or forefoot surgery?
That is the objective. The purpose of reconstruction is not simply to improve the appearance of an X-ray; it is to correct the structural problem in a way that allows the patient to return to meaningful daily activity.
What “normal” means is different for every person. For one patient it may mean running or tennis. For someone else it means wearing professional shoes comfortably, traveling, walking without planning around pain, or remaining independently mobile.
That is why I prefer to define those goals before surgery rather than waiting until afterward to ask what the patient hoped to regain.
Will I be able to wear regular shoes?
Across the forefoot procedures I perform, more than 90% of my patients transition back into shoes within approximately 2–4 weeks, although the timing for an individual patient depends on the procedure, swelling, biology, and recovery plan.
That early transition is only part of the story. The longer-term goal is to create a foot that gives the patient more useful footwear options than the painful deformity allowed beforehand.
I do not promise that every foot will tolerate every style of shoe, but footwear goals are absolutely worth discussing before reconstruction.
For the detailed timing of footwear and other recovery milestones, see the complete foot surgery recovery timeline.
Will I be able to exercise again?
For patients who are appropriate surgical candidates, treatment is generally designed with a return to meaningful activity in mind.
Walking, cycling, strength training, golf, tennis, and running all place different demands on a reconstructed forefoot, so return to activity has to be progressive and specific to what the patient is trying to do.
I prefer to know those goals before surgery so they can be considered during both reconstruction and recovery planning.
Will my foot look normal after surgery?
Appearance matters, particularly with visible deformities such as bunions and hammertoes.
My goal is a correction that is structurally sound, functional, and as natural appearing as reasonably possible. Minimally invasive access points can also reduce the scar burden compared with larger surgical exposures.
No surgeon should promise a perfectly shaped foot or an invisible scar. Anatomy, severity of deformity, swelling, skin quality, healing biology, and the reconstruction itself all influence the final appearance.
Can older patients return to independent living after foot surgery?
Age by itself does not determine whether someone is an appropriate candidate. I care much more about overall health, circulation, healing capacity, baseline strength and balance, the procedure required, and what the patient wants to preserve.
For many older adults, the most important goal is maintaining the ability to walk, shop, travel, drive, care for a spouse, or live independently. When the reconstruction safely permits protected mobility, preserving that mobility can be particularly valuable because we want to avoid unnecessary loss of strength and function during recovery.
Will I still need orthotics after surgery?
Some patients will.
Surgery corrects structural deformity, but the reconstructed foot still has to accept and transfer load for years afterward. Custom orthotic support can be valuable when it helps distribute pressure, support the mechanics created by surgery, or protect the reconstructed forefoot during long-term activity.
Whether orthotics are appropriate depends on the patient’s mechanics and the reconstruction performed.
Does minimally invasive surgery mean I get back to life faster?
In my experience, minimizing unnecessary surgical disruption can meaningfully change the recovery experience. My bunion procedures are designed around immediate protected walking, and more than 90% of my forefoot patients transition back into shoes within approximately 2–4 weeks.
Those are meaningful functional milestones, but they do not mean biological healing is complete at two or four weeks.
The actual trajectory still reflects what was corrected, the patient’s healing capacity, and the recovery system designed around both.
How do I know what life after surgery would look like for me?
That is one of the most important purposes of a surgical consultation.
A useful consultation should not stop at identifying the diagnosis. We should discuss your work, exercise, footwear, travel, caregiving responsibilities, health and healing factors, and what you are most concerned about losing during the recovery.
From there, we can determine whether surgery makes sense and, if it does, what the journey back to your life is likely to require.
Your Life Is the Outcome
When I evaluate a surgical result, I care about alignment, bone healing, stability, mechanics, and the quality of the structural correction. Those are the foundations of a good reconstruction.
But they are not the final question.
The final question is what that corrected foot allows the patient to do.
Can you walk without planning around it? Can you wear the shoes you want to wear? Can you travel, exercise, work, care for your family, and preserve the independence that matters to you?
Those are not “soft” outcomes.
They are the reason the structural outcomes matter.
If your main concern is the practical timeline for walking, shoes, work, driving, swelling, and exercise, read the complete foot surgery recovery timeline.
If you want to understand why I integrate the correction with healing, stability, mechanics, and recovery rather than treating those as separate problems, learn how PRISM™ goes beyond minimally invasive surgery.
If you are still deciding whether your bunion has begun taking enough from your life to justify intervention, start with the Complete Bunion Decision Guide: When to Wait and When to Act.
And if you are ready to understand what treatment and life afterward could realistically look like for your particular foot, schedule a discovery call with Dr. Michael Tagge.